


This piece was co-written by Dr Salma Abdalla and is also cross-posted here.
Public health is in a time of challenge. During the pandemic, public health came to be seen as aligned with particular partisan interests, which led to an erosion of the public’s confidence in what we do. Complicating the moment, the new federal administration has imposed changes on the public health system that have further eroded confidence in public health among much of the public and made an evidence-based consensus increasingly difficult to achieve. Last month, we introduced the Purple Public Health Project as a response to this challenge, aiming to rebuild public health’s legitimacy, and the public’s trust in us, through both genuine ideological openness and clarity of purpose. Each month this year, we will engage with a topic that points towards a more heterodox public health. This engagement will include a Substack essay, a podcast conversation, suggested readings, a teaching guide, and more. Material related to the project can be found here.
The project’s ethos is, at core, an effort to address a central question: what is public health for? Are we a special interest group, a pipeline between politicians and the think tanks and academic institutions with which their ideas and policies align? Are we for serving just those who are already inclined to agree with us? Or are we for something else – something broader, deeper, more inclusive in our pursuit of a healthier world for all?
This month’s Purple Public Health topic, then, is an effort to answer the question, “what is public health for?” Doing so means engaging with the field at its most fundamental level, where public health thinking is conceived and actualized. Public health rests on two essential pillars, both core to its function: academic public health and public health practice. Understanding what public health is for means understanding what these domains do and the occasional tension they navigate as they engage with the values and data that drive our work.
Academic public health generates data through a process of rigorous scientific inquiry into the causes of health and disease and the effectiveness of interventions. The aim of this work is fact-driven inquiry that produces data and policy options without necessarily prescribing what society should do with this information. But academic public health does not stop at generating data. It also interprets it through ethical frameworks and urges action towards achieving public health goals, aiming to align societal values with health imperatives (e.g. valuing prevention, solidarity, and equity). This complements academic public health’s empiric commitments by articulating the goals we should collectively pursue to create better health for all.
These domains, the scientific and the values-driven, are both essential, yet must remain conceptually separate for our work to maintain credibility. The processes of evidence generation and value promotion demand different approaches and guardrails. Public health scientists must keep objective analysis separate from advocacy to ensure that data are not distorted by ideology. Likewise, value-driven discussions should be transparent about what they are, rather than present themselves as “the science.” This clear separation helps preserve the integrity of research and ensures values arguments are respected for what they are rather than distrusted for posing as what they are not.
The line between values- and data-driven actions presents a similar complication for public health practice. Public health agencies and professionals that do much of the work of practice build on academia’s work in two key ways: by implementing data-informed programs and policies, and by advancing values-based messaging and norms. This can lead to more values-data tension. On one hand, health departments use research evidence to design interventions (for example, using epidemiological data to shape vaccination campaigns or environmental health regulations). On the other hand, they engage in trying to influence community values and behaviors (for example, crafting messaging that emphasizes collective responsibility for health, or establishing norms around issues like smoke-free environments). In doing their work, practitioners must integrate evidence and values without conflating them – values may guide where and how data are deployed, but the public should never be unclear about whether we are engaging from a place of judgment or fact.
In both academic public health and public health practice, we can face the challenge of conflating data and values, of our efforts becoming too ideological at the expense of the rigor that should inform our science and the inclusivity that should characterize our engagement with communities. Mixing up the domains of values and data, treating value judgments as facts, or vice versa, undermines public health’s legitimacy and effectiveness, especially in polarized contexts. When public health science is perceived as a cover for political or moral agendas, trust in the data falls. Conversely, when we claim a values-based position is simply a matter of settled “science,” we fail to have honest value debates. Clarity and honesty in keeping these spheres separate fortifies public health’s authority, helping us to more effectively support the health of the whole population – which is what we are for.
Of course, we may say “this is all well and good in the abstract, but what about when the rubber meets the road of making policy in a messy, polarized world?” Let us tackle this question in the context of three real-world examples.
Gun violence research and work
Public health research provides robust data on firearm risks and interventions. For example, evidence shows that certain gun regulations can reduce injuries and save lives. However, gun policy is also deeply entwined with core American values such as individual rights and liberty. Second Amendment advocates often view public health gun control proposals not as neutral safety measures but as value-laden attacks on personal freedom. This tension means that if public health experts present gun restrictions as purely data-driven necessities, we run into public skepticism and political backlash from those who prioritize gun rights. Successful navigation of this issue requires acknowledging both the empiric findings and the value debates. We can provide factual impact analysis, while separately engaging in an open, values-based dialogue about rights, responsibility, and safety. Only by keeping these threads clear can public health avoid feeding perceptions of partisanship and, instead, inform a constructive policy discussion.
Obesity policy and the “nanny state” debate
There is strong evidence that policies like sugar-sweetened beverage taxes can improve health outcomes by reducing consumption. Yet, interventions along these lines can trigger the “nanny state” objection - the argument that public health is overstepping by infringing on personal choice and autonomy. Critics, sometimes supported by industry interests, frame such measures as paternalistic government control (e.g. “the government is telling us what to eat or drink”). This exemplifies a values clash: public health values population well-being and prevention, whereas some opponents value individual freedom and limited government. If health officials present their data with a tone of strident moral urgency (coming across as preachy or coercive), they risk alienating segments of the public who feel their lifestyle choices are under attack. A better approach is to keep the empiric rationale separate, clearly communicate the health data (e.g. obesity rates, costs, the effectiveness of interventions), while also respectfully addressing values-based concerns (emphasizing personal agency, fairness, and why society has an interest in healthier choices). By clearly partitioning “the evidence for action” from the debate about “the role of government,” public health can make its case without falling into ideological traps, thereby maintaining legitimacy even among skeptics.
Harm reduction initiatives.
Public health has championed harm reduction strategies (such as needle exchange programs, opioid overdose prevention sites, and drug decriminalization) because evidence shows some of these approaches save lives and reduce disease transmission. However, harm reduction is often controversial due to moral and cultural values surrounding drug use. Some community members or policymakers view approaches like safe injection sites as enabling immoral behavior or “sending the wrong message,” preferring an abstinence-only stance rooted in their values. Notably, even within the harm reduction movement, there has been debate on how to present the case – whether to use a value-neutral, scientific framing (focusing on cost-benefit and outcomes) or an openly moral framing (emphasizing compassion and human rights). Keeping empiric claims distinct (e.g. “This program reduces harm by X%”) from value appeals (e.g. “We believe every life is worth saving, regardless of drug use”) allows health officials to build broader support. If they were to blur the two – for instance, by overstating the data to win a moral argument or dismissing opponents as simply “ignoring science” – they could further polarize the issue and lose credibility. A clean separation between facts and values here can help in finding common ground, or at least mutual respect, even amid polarization.
We end by returning to our central question: what is public health for? Public health is for creating better health for all. It does this by doubling down on its dual commitments: uncompromising scientific rigor in generating data, and earnest, transparent engagement with values in shaping discourse and policy. In a polarized world, a “purple” public health approach – one that speaks to everyone by presenting evidence objectively while also addressing diverse value perspectives openly – offers a path to rebuilding credibility. By being mindful of our core purpose in both realms, public health can better unite communities behind effective actions and continue its mission of improving population well-being without political or ideological distortion. The charge, moving forward, is to remain both scientifically sound and values-conscious, while never confusing the two.
__ __ __
A databyte
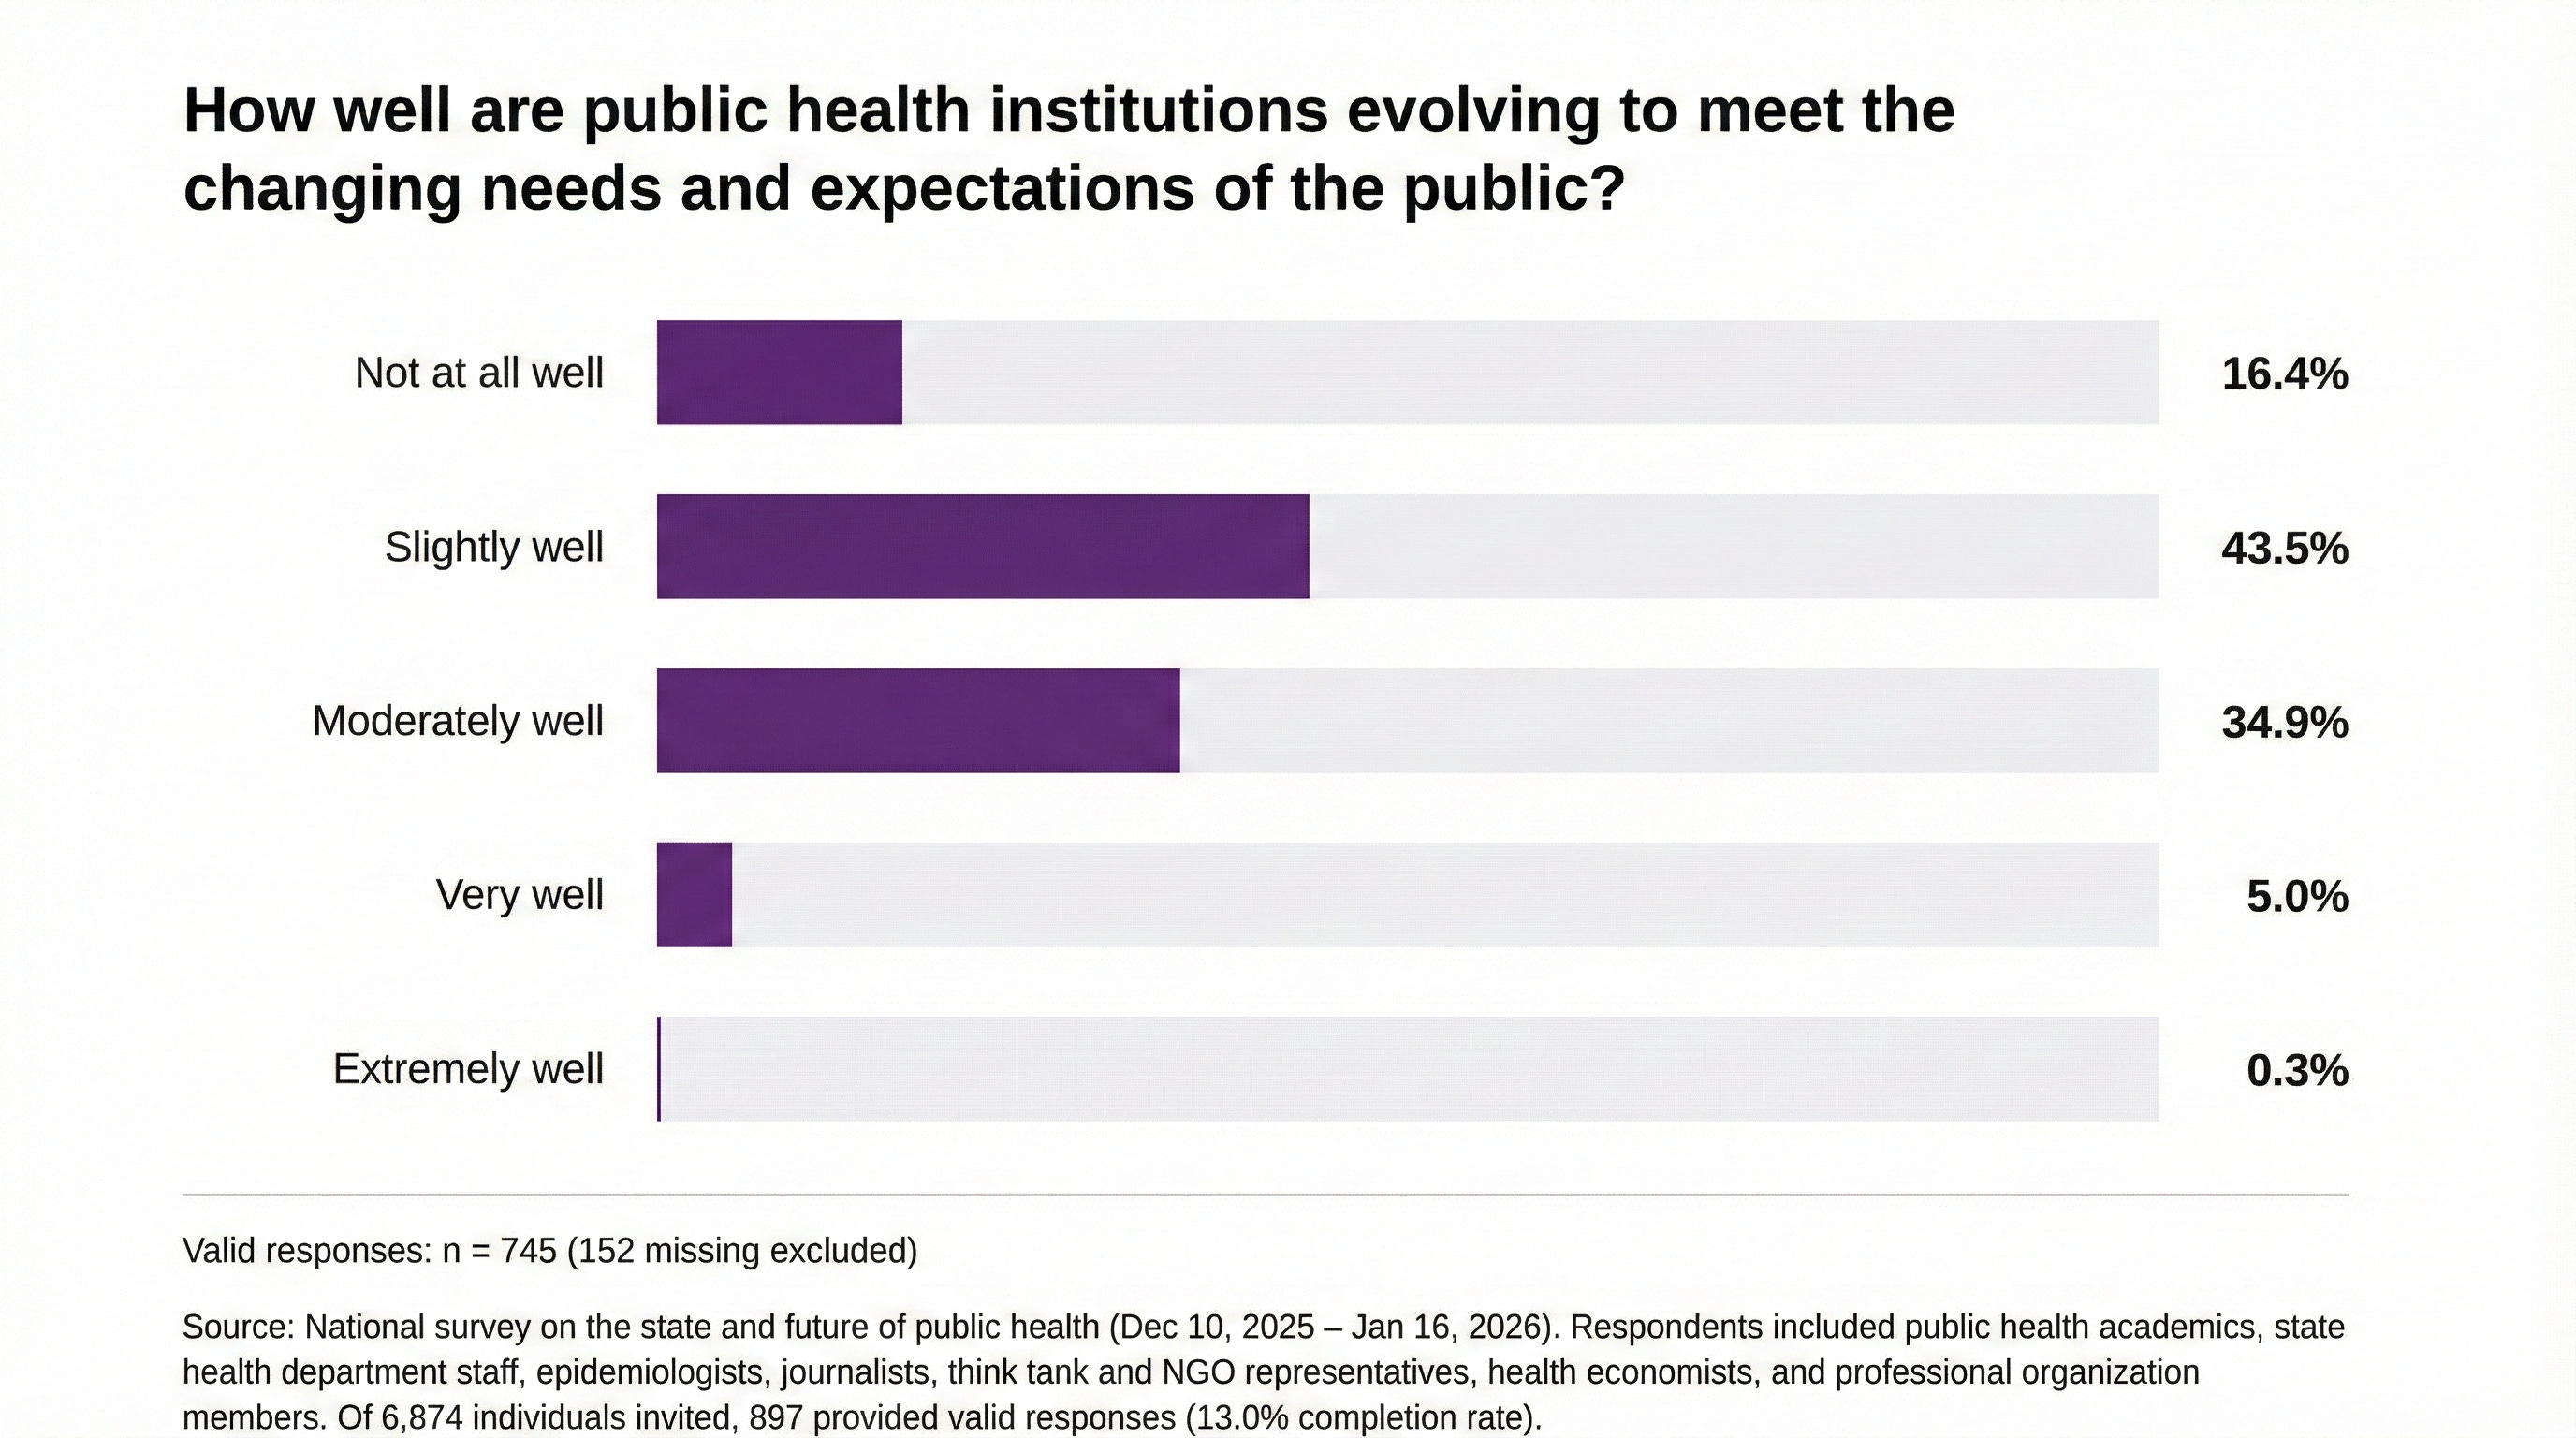
In a national survey we conducted recently of public health experts, nearly 60% of respondents said public health institutions are evolving only ‘slightly well’ or ‘not at all well’ to meet the changing needs of the public. These results suggest the field itself recognizes the need for reimagination and may be ready for it. Full survey results will be released later this year.
__ __ __
The Purple Public Health Project
This piece is part of the Purple Public Health Project. The Purple Public Health project is a multiyear, multimedia effort to re-establish public health’s legitimacy, broaden its reach, and shore up its foundations in this moment and beyond. The project engages with topics that are core to shaping a more heterodox public health. Previous essays and other material related to the project are available on the Healthier Futures Lab webpage. Suggested readings, a teaching guide, and other material related to this month’s topic can be found here.
__ __ __
Also this week
In JAMA Health Forum:
A Role for Market Forces in US Health Care-Principles and Guardrails
Spoke with Daniel Vergano in Scientific American about changes in federal health institutions over the last year.

"Public health rests on two essential pillars, both core to its function: academic public health and public health practice."
That statement made me curious. Where do the people most affected (people with lived experience) by the research and the practice fit into this conversation? I would think that including them in both pillars would help increase trust.